Investigating Outbreaks: Epidemiology
You'll be able to trace an outbreak from index case to contacts using a simple data set.
How epidemiologists trace an outbreak back to its source, and what the data has to show before they act.
Printable Worksheets
Print or save as PDF, or build a custom worksheet from any module's questions.
How are vaccination, antibiotics, and handwashing connected in preventing disease?
How can lower local vaccination coverage affect transmission if an infection is introduced, and what else affects whether an outbreak grows?
● Know
- Define epidemiology and key terms such as outbreak, case, and incidence
- Identify the data streams epidemiologists use to track an outbreak
- Describe how contact tracing follows a pathogen through a population
● Understand
- Explain how multiple data streams are combined to locate an outbreak source
- Interpret case and incidence data to judge whether an outbreak is growing or slowing
- Connect a fictional measles investigation to the wider science of disease tracing
● Can do
- Trace an outbreak from index case to contacts using a simple data set
- Read and analyse incidence graphs to describe outbreak trends
- Evaluate how data and public health responses can help control an outbreak
The Disease unit is built around a single narrative arc: what disease is, how it spreads, how the body fights it, how we prevent and treat it, and how society responds. Every concept you have learned fits into this arc somewhere. Pathogens and transmission explain the cause and spread. The three lines of defence explain the biological response. Vaccines and antibiotics explain prevention and treatment. Public health and epidemiology explain the population-level response.
The connections between concepts are just as important as the concepts themselves. Vaccination coverage can influence community immunity, but it is not the same as the proportion effectively immune. Antibiotic misuse drives resistance through natural selection. Social determinants shape health outcomes across populations. Global connectivity determines pandemic potential. A student who can trace these connections has mastered the unit; a student who knows only isolated facts has not.
Text description
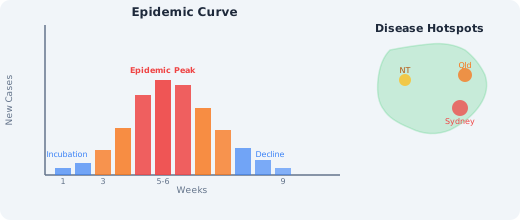
- Bars show new cases each week for 12 weeks.
- Weeks 1–2: few cases (incubation). Cases then rise to a peak at weeks 6–7.
- From week 8 cases decline, back to a few by week 12.
- Map of Australia: disease hotspots at Sydney, in Queensland and in the Northern Territory.
To explain why measles outbreaks occur in wealthy countries with strong healthcare, a synthesising student connects: imported case (global travel) + low local coverage (vaccine hesitancy) + high R₀ (pathogen trait) = outbreak. No single factor explains it; the interaction does.
The Australian Curriculum Assessment and Reporting Authority (ACARA) identifies systems thinking as a key capability in science, recognising that modern challenges like pandemics and climate change require understanding connections, not just facts.
- Vaccination
- Antibiotic overuse
- Social determinants
- R₀ (basic reproduction number)
- Herd immunity
- Health disparities
- Antimicrobial resistance
- Herd immunity threshold
The simplified herd-immunity threshold is the immune fraction 1 − 1/R₀. It assumes complete, lasting immunity and equal mixing. In this model, R₀ = 2 gives a threshold of 50%, R₀ = 4 gives 75%, R₀ = 10 gives 90%, and R₀ = 15 (measles) gives about 93%. These are model immune fractions, not vaccination-coverage requirements or guarantees about an outbreak. If effective immunity is below the threshold, average onward transmission can be above one under the model assumptions; the formula alone does not give the probability or size of a real outbreak. Vaccination coverage and effective immunity are not identical. The Australian Immunisation Handbook emphasizes maintaining high measles immunity to reduce outbreak risk and sustain elimination. See the Australian measles guidance.
Real-world transmission also depends on how immunity is distributed, patterns of contact, whether infection is introduced, and public-health response. For example, CDC surveillance guidance describes measles outbreaks involving imported cases and susceptible contacts, including close-knit under-vaccinated communities. Lower coverage can leave more people susceptible and increase the opportunity for spread, but a coverage percentage alone cannot predict whether an outbreak will occur or how large it will be. Read the CDC measles surveillance overview.
In the simple model, an immune fraction near 93% brings average onward transmission to one for R₀ ≈ 15. A lower immune fraction can allow transmission to grow after an introduction, while a higher fraction reduces average spread under the model assumptions. In real communities, local immunity gaps and contact patterns matter; these thresholds alone do not predict outbreak frequency or size.
Australian health guidance emphasizes maintaining high measles immunity to reduce outbreak risk and sustain elimination. Coverage is one indicator of population protection; it does not by itself classify a community as ‘protected’ or ‘vulnerable’ or predict an outbreak. Australian Immunisation Handbook: Measles.
A fair method is the backbone of any scientific investigation. Fairness means that the only thing differing between your experimental groups is the independent variable you are testing. In a simulation testing whether temperature affects bacterial growth, temperature is the only factor that should change. The culture examples below are simulated data for method evaluation, not instructions to grow bacteria. Any real school culture investigation requires teacher approval, an identified school-approved organism, appropriate containment and disposal, and incubation at no more than 30°C. Everything else, type of bacteria, amount of nutrient, container size, light exposure, incubation time, must be identical across all groups. These unchanged factors are called controlled variables.
Reliability means your results are consistent and repeatable. You achieve reliability by using multiple replicates, several identical trials at each condition, and by measuring precisely. A single petri dish at each temperature tells you almost nothing, because the result might be a fluke. Three or more replicates let you see whether a pattern is real or random. Precise measurements (using a ruler with millimetre marks rather than eyeballing) reduce uncertainty and strengthen your conclusions.
A computer simulation includes random variation in bacterial growth and models 20°C and 25°C using one virtual petri dish per temperature. The virtual 25°C dish shows more growth, but a single trial cannot rule out chance. With five virtual dishes per temperature, the student can calculate an average and see whether the difference is consistent.
The CSIRO Education program provides free resources on experimental design for schools, emphasising that the difference between a demonstration and an experiment is the control of variables.
Wrong: "A depth study is just a long essay about a disease." No, a depth study is an investigation. It requires you to ask a question, gather evidence, analyse data, and draw conclusions. It is active science, not just research.
Right: A depth study is an active scientific investigation that requires asking a question, gathering evidence, analysing data, and drawing conclusions. It is not just a research essay.
Wrong: "The different topics in this unit have no connection to each other." No, they are deeply connected. Pathogens cause disease, which the immune system fights, which vaccines train, which antibiotics treat, which resistance limits, which public health prevents. Every topic links to others.
Right: All topics in this unit are deeply connected: pathogens cause disease, which the immune system fights, which vaccines train, which antibiotics treat, which resistance limits, which public health prevents.
Wrong: "Once you memorise facts about disease, you understand it." No, true understanding means being able to explain connections, apply concepts to new situations, and evaluate evidence. Facts are tools; understanding is the ability to use them.
Right: True understanding means being able to explain connections between concepts, apply them to new situations, and evaluate evidence. Facts alone are not enough without the ability to use them.
Australian Scientists Fighting Disease
Professor Fiona Stanley (AC): An Australian epidemiologist who founded the Telethon Kids Institute in Perth. Her research on birth defects, Indigenous health, and population health methods transformed Australian public health. She championed the use of population data to guide health policy.
Professor Ian Frazer: Co-developer of the HPV vaccine at the University of Queensland. His work has prevented countless cases of cervical cancer worldwide and put Australia on track to eliminate cervical cancer entirely.
Modern Australian research: Today, Australian scientists at WEHI, the Doherty Institute, CSIRO, and universities across the country continue to fight disease. During COVID-19, Australian researchers contributed to vaccine development, genomic surveillance, and long COVID research. Aboriginal and Torres Strait Islander researchers are increasingly leading health research that addresses community priorities with cultural authority.
✍ Copy Into Your Books
▾Unit Connections
- Pathogen -> Transmission -> Defence -> Treatment
- Infectious vs non-infectious disease
- Local, national, and global perspectives
Key Formulas
- Herd immunity threshold ≈ 1 - 1/R0
- Incidence rate = (new cases/population) × multiplier
- Case fatality rate = (deaths/cases) × 100%
Depth Study Steps
- Choose topic -> Formulate question -> Research -> Hypothesis -> Method -> Data collection -> Analysis -> Conclusions -> Communication
Concept Connections
Depth Study Planning
At the start of this lesson, you considered a fictional measles investigation in which a public health team uses vaccination records, hospital information and contact histories to look for links between cases. The scenario illustrates how multiple layers of disease prevention work together.
Now that you've worked through the lesson, why is it useful to compare vaccination records, hospital information and contact histories? Which source might be incomplete on its own, and how could another source help investigators check it?
Q1. Define epidemiology and explain the difference between incidence and prevalence, using an example. (2 marks)
Q2. In the fictional classroom measles investigation, the public health team combines three data streams (vaccination records, hospital information, and contact histories). Explain why using several data streams together is more reliable than relying on just one. (3 marks)
Q3. An epidemiologist is given a graph showing new measles cases each week. Describe the steps you would take to interpret the epidemic curve and decide whether the outbreak is growing or slowing. (3 marks)
Revisit Your Thinking
Go back to your Think First answer. Has your understanding changed?
- How has your understanding of disease and health developed across this entire unit?
- What connections between concepts do you find most powerful or surprising?
Model answers (click to reveal)
Answers
▾MCQ 1
B Epidemiology is the study of how diseases spread through populations and the factors that influence how often they occur. It looks at patterns across groups of people, not the treatment of a single patient.
MCQ 2
A The index case is the first recognized or reported case in an investigation. It is not necessarily the primary case (the first person infected) or the source case (the person or exposure that started transmission). An index case may have been infected by someone whose illness was never recognized, so investigators use interviews, timelines and other evidence to work out how transmission began.
MCQ 3
C The peak of an epidemic curve is the point where the largest number of new cases was recorded in a single period. After the peak, the number of new cases usually declines.
MCQ 4
D Contact tracing identifies and follows up the people an infected person has been near, so they can be tested or isolated before they spread the disease further.
MCQ 5
B Incidence is the number of new cases appearing over a set period of time. Prevalence is the total proportion of a population that has the disease at one point in time.
Short Answer 1
Model answer: Epidemiology is the study of how diseases spread through populations and the factors that influence how often they occur. Incidence counts the number of new cases of a disease that appear in a population over a set period, for example 40 new measles cases in Sydney during one month. Prevalence is the total proportion of the population that has the disease at a given moment, for example all the people currently infected with measles on a single day. Incidence measures how fast new cases are appearing, while prevalence measures how widespread the disease is at one point in time.
Short Answer 2
Model answer: Using several data streams together is more reliable because any single source can be incomplete or misleading. Vaccination records show who was unprotected but not who actually became sick. Hospital admissions show severe cases but miss mild ones treated at home. Contact-tracing maps show who was exposed but rely on people remembering their movements. By combining all three in this fictional investigation, the team can cross-check information: gaps in one stream may be filled by another, and possible links between cases can be assessed with greater confidence. The data can help investigators develop and test explanations for how the outbreak spread.
Short Answer 3
Model answer: First, read the axes carefully: the horizontal axis usually shows time (weeks) and the vertical axis shows the number of new cases. Second, identify the overall shape, noting where cases first rise, where the peak (highest bar) occurs, and whether the curve falls again afterwards. Third, compare the most recent bars with earlier ones: if the number of new cases each week is still rising, the outbreak is growing; if the bars are getting shorter week by week, the outbreak is slowing. Finally, link the trend to the public-health response, since a falling curve after contact tracing and vaccination suggests the control measures are working.