Vaccination, Active and Passive Immunity
You'll be able to classify types of immunity using a two-axis framework.
In 1955, Jonas Salk announced a working polio vaccine. Within two years, polio cases in the US dropped by 85–90%. A disease that had paralysed hundreds of thousands of children per year, including a future US president, was being dismantled by a syringe. This lesson is about how that is possible, and why it sometimes isn't.
Orient yourself
Warm up on earlier material, predict what mass vaccination does to a population, then scan the goals and vocabulary.
Three quick questions from earlier lessons. Pulling old material back to mind before you learn something new makes the new material stick better, so this is not busywork.
Practise this lesson
Four printable worksheets that build from the foundations up to exam-style questions, start at whatever level suits you.
In 1952, the United States recorded 57,879 polio cases, the worst outbreak in American history. Children were placed in iron lungs to breathe. Pools, cinemas, and libraries closed every summer in fear. By 1961, cases had fallen to 161.
Before reading: what do you think a successful mass vaccination program actually does to a disease at the population level, not just the individual level? How does vaccinating individuals change the fate of the pathogen itself?
Know
- The distinction between active and passive immunity
- Natural vs artificial forms of each
- How herd immunity works and the thresholds for common diseases
- Why vaccination programs sometimes fail to achieve eradication
Understand
- Why herd immunity protects those who cannot be vaccinated
- Why vaccine hesitancy undermines herd immunity at the population level
- The difference between elimination, eradication, and control
Can Do
- Classify types of immunity using a two-axis framework
- Evaluate the effectiveness of vaccination programs using data
- Explain herd immunity threshold calculations
Four kinds of immunity
Place any example on the two axes, active or passive and natural or artificial, then explain why passive protection fades.
Core Content
Natural vs artificial × active vs passive
After Jonas Salk's 1955 polio vaccine trial, a vaccinated child who had never encountered poliovirus had measurable antibodies in their blood and long-lived memory lymphocytes, without ever being sick. A newborn infant in the same year had maternal IgG antibodies crossing the placenta, providing immediate protection against infections the mother had encountered, without the infant's own immune system having done anything. Two very different mechanisms of protection, both real. The classification framework explains why they work differently.

The two-axis framework, always classify immunity by both axes: active vs passive, AND natural vs artificial
Classify immunity on two axes. Active = your own immune response → forms memory; slow onset; long-lasting. Passive = pre-formed antibodies transferred in; immediate; no memory; temporary. Crossed with source: natural active = infection; artificial active = vaccine; natural passive = maternal antibodies (placenta/breast milk); artificial passive = antivenom/immunoglobulin injection.
Pause, copy the four immunity types (active/passive × natural/artificial) with an example of each into your book.
Receiving pre-formed antibodies as an injection (e.g. antivenom) provides which type of immunity?
Annotated Diagram, The Four Types of Immunity
Pattern A, Draw and Annotate
In your book, draw and annotate a diagram showing all four types of immunity using the two-axis framework (active/passive × natural/artificial). For each quadrant:
- Name the type of immunity.
- Give one specific example.
- State whether memory cells are formed.
- State the approximate duration of protection.
- Identify one situation where this type of immunity would be the most appropriate protection strategy.
Protection you get from other people
Use R₀ and the 1 − 1/R₀ threshold to work out how much coverage a disease actually needs.
Breaking transmission chains by coverage
We just saw that active immunity (especially vaccination) protects the individual. That raises a question: what happens when most of a population is immune at once? This card answers it → herd immunity, and how the R₀ sets the threshold needed.
When enough individuals are immune, transmission chains break, even susceptible individuals are protected because the pathogen cannot find enough hosts to spread.

Herd immunity protects unvaccinated individuals by surrounding them with immune people, the pathogen cannot find a transmission chain
Herd Immunity Thresholds
The proportion of a population that must be immune to achieve herd immunity depends on the pathogen's basic reproduction number (R₀) the average number of people one infected person infects in a fully susceptible population. The higher the R₀, the higher the immunity threshold required.
| Disease | R₀ (approx.) | Herd Immunity Threshold | Status |
|---|---|---|---|
| Measles | 12–18 | ~95% | Eliminated in many countries; outbreaks where coverage drops |
| Polio | 5–7 | ~80–85% | Near-eradicated globally; endemic in Pakistan and Afghanistan |
| Smallpox | 5–7 | ~80–85% | Eradicated 1980 |
| COVID-19 (original strain) | 2–3 | ~50–67% | Threshold raised by variants with higher R₀ |
| Influenza (seasonal) | 2–3 | ~50–67% | Annual vaccination required due to antigenic variation |
| Pertussis (whooping cough) | 12–17 | ~92–94% | Resurgent in populations with declining booster rates |
Herd immunity = enough immune individuals to break transmission chains. The threshold = 1 − (1/R₀), so a higher basic reproduction number (R₀) needs a higher threshold, measles (R₀ 12–18) needs ~95%, polio (R₀ 5–7) needs ~80–85%. It protects those who can't be vaccinated (newborns, immunocompromised).
Pause, copy the herd-immunity definition and the threshold formula 1 − (1/R₀) into your book.
The herd immunity threshold is calculated as 1 − (1/R₀), where R₀ is the basic _____ number.
In the simulator set R0 = 2.0 with nobody immune and population 2 000, then press Run 200 outbreaks. Roughly how many of those 200 die out early, even though Re starts at 2.0?
Run one outbreak in the simulator at R0 = 4.0 with nobody immune. It ends with people still uninfected, and the simulator explains that Re fell because S/N fell, while R0 itself never _____.
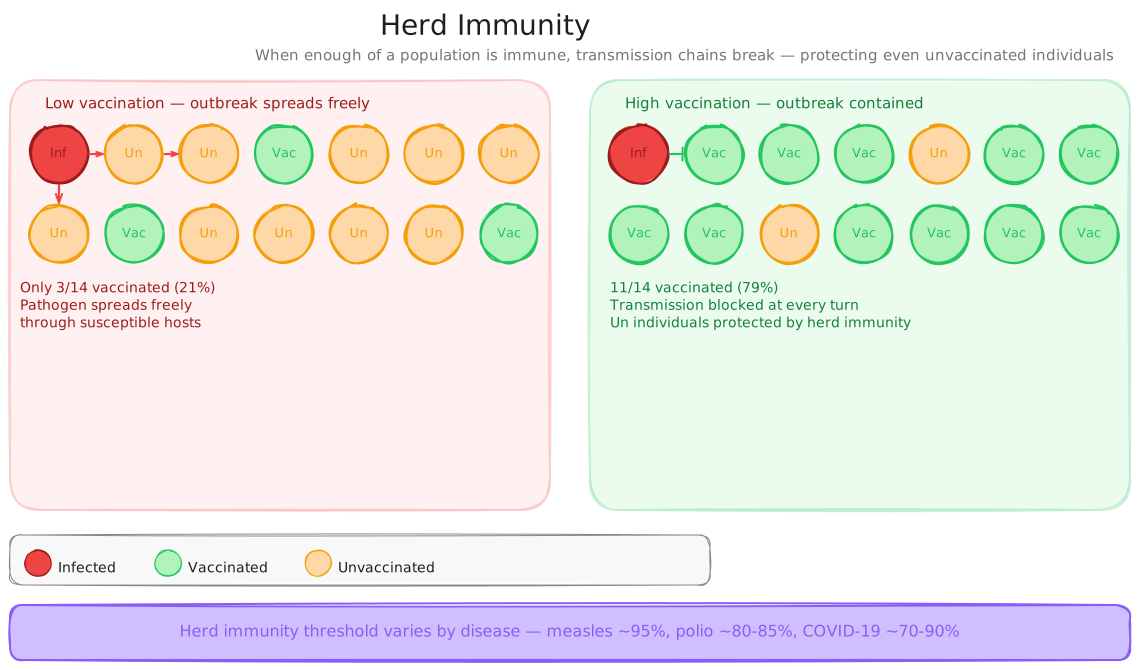
Herd Immunity Population Diagram
Control, elimination, eradication
Separate three terms people use loosely, then judge with real data why so few diseases are ever eradicated.
Control · elimination · eradication
We just saw that herd immunity depends on coverage and R₀. That raises a question: what is the actual end goal of a vaccination program, and why have we eradicated only one human disease? This card answers it → control vs elimination vs eradication, and the barriers to eradication.
Vaccination programs can achieve three levels of disease control, depending on coverage, vaccine effectiveness, and pathogen characteristics.
Control
Elimination
Eradication
Why Some Diseases Cannot Be Eradicated
Eradication is extraordinarily difficult. The conditions that allowed smallpox eradication were almost uniquely favourable: no animal reservoir, obvious visible symptoms, a stable highly effective vaccine, and a virus that did not mutate rapidly. Diseases that resist eradication typically have one or more of the following features:
- Animal reservoirs: Influenza circulates in birds and pigs; even if humans were fully immune, the virus would survive in animal populations and re-emerge (zoonotic re-introduction)
- Rapid antigenic variation: HIV and influenza mutate fast enough that existing immunity does not prevent new strains
- Long asymptomatic period: HIV-infected individuals may not know they are infected and can unknowingly transmit for years
- Geopolitical barriers: Polio persists in regions where vaccination campaigns are impeded by conflict, distrust, or logistical collapse
- Vaccine limitations: Some vaccines (e.g. current influenza vaccines) provide imperfect or short-lived immunity, requiring annual re-vaccination
Three levels of disease control: control = reduced incidence, disease still present; elimination = zero cases in a defined area but the pathogen exists elsewhere; eradication = permanent global zero (only smallpox, 1980). Barriers to eradication: animal reservoirs, rapid antigenic variation, long asymptomatic spread, and geopolitical obstacles.
Pause, copy control vs elimination vs eradication and the barriers to eradication into your book.
Smallpox is the only human disease ever:
Evaluate vaccination program evidence
Analyse measles coverage, then use polio evidence to judge what sustained vaccination achieves.
Data Analysis, Measles Cases and Vaccination Coverage
Pattern A, Structured Data Analysis
The table below shows measles vaccination coverage and annual case numbers in a hypothetical country over 15 years.
| Year | Vaccination coverage (%) | Measles cases (annual) |
|---|---|---|
| 1 | 55 | 8,200 |
| 3 | 68 | 4,400 |
| 5 | 80 | 1,100 |
| 7 | 88 | 310 |
| 9 | 95 | 12 |
| 11 | 97 | 3 |
| 12 | 91 | 480 |
| 13 | 89 | 1,240 |
| 14 | 93 | 210 |
| 15 | 96 | 8 |
- Describe the trend in measles cases between Years 1 and 11. What does this suggest about the effectiveness of the vaccination program during this period?
- Between Years 11 and 13, vaccination coverage dropped from 97% to 89% and cases rose from 3 to 1,240. Explain why a drop of only 8 percentage points in coverage produced such a dramatic increase in cases, referring to the concept of herd immunity threshold.
- The measles herd immunity threshold is approximately 95%. Using Years 9–11 (coverage ≥95%) and Years 12–13 (coverage 89–91%), explain how crossing this threshold in either direction affects disease transmission.
- By Year 15, coverage had recovered to 96% and cases fell to 8. Has the country achieved elimination? Justify your answer using the definition of elimination and the data provided.
- A government advisor suggests discontinuing the measles vaccination program once coverage consistently reaches 97% for three years. Evaluate this recommendation.
Polio was one of the most feared diseases of the 20th century, largely because it preferentially struck children, was highly visible (iron lungs, leg braces, wheelchairs), and had no effective treatment. Franklin D. Roosevelt, who contracted polio in 1921, co-founded the National Foundation for Infantile Paralysis in 1938, later renamed the March of Dimes after comedian Eddie Cantor suggested Americans send their dimes directly to the White House. The campaign raised millions for research and directly funded Jonas Salk's work on an inactivated polio vaccine. On April 12, 1955, exactly ten years after Roosevelt's death, Salk's vaccine was declared "safe, effective, and potent." Americans wept in the streets. Church bells rang. Within two years, polio cases dropped by 85–90%. By 1961, Albert Sabin's oral attenuated vaccine was licensed, easier to administer globally. Polio has since been eliminated from every country except Pakistan and Afghanistan, where vaccination campaigns continue despite security challenges.
The gap between 350,000 cases per year and fewer than 100 is a direct measure of what sustained vaccination programs achieve at the population level. You will evaluate vaccination program effectiveness using data in Activity 2 and Short Answer Q3.
Consolidate population immunity
Correct the common errors, collect the key distinctions, then test the herd immunity threshold.
Active vs Passive Immunity
- Active: own immune response → memory formed; slow onset; long-lasting.
- Passive: pre-formed antibodies transferred; immediate; no memory; temporary.
- Natural active = infection. Artificial active = vaccine.
- Natural passive = maternal antibodies. Artificial passive = antivenom/Ig.
Herd Immunity
- When enough immune individuals break transmission chains.
- Threshold = 1 − (1/R₀).
- Higher R₀ → higher threshold (measles: 95%; polio: 80–85%).
- Protects those who cannot be vaccinated (newborns, immunocompromised).
Levels of Disease Control
- Control: reduced incidence; disease still present.
- Elimination: zero cases in a defined area; pathogen still elsewhere.
- Eradication: permanent global zero, only smallpox achieved.
Why Eradication Is Difficult
- Animal reservoirs (influenza in birds/pigs).
- Rapid antigenic variation (HIV, influenza).
- Asymptomatic transmission (HIV, polio).
- Geopolitical barriers (polio in Pakistan/Afghanistan).

Herd Immunity, High vs Low Coverage
Distinguish between active and passive immunity, and between their natural and artificial forms.
This dot point is vaccination, including passive and active immunity. Distinguish requires an explicit criterion at each level, and there are two levels here — four categories arise from two independent questions.
Plan: state the two criteria, apply the first, apply the second, then show what the combination predicts.
The first question is whose immune system produced the antibodies: active immunity means the individual's own immune system responded and produced them, while passive immunity means antibodies made elsewhere were transferred in. The second question is how the exposure occurred: naturally, through ordinary living, or artificially, through deliberate medical intervention.
The consequences of the first criterion are large. Active immunity involves clonal selection, so memory cells are produced and protection is long-lasting, often lifelong — but it takes days to weeks to develop and requires the individual to mount a response, so it does not help someone already exposed. Passive immunity provides ready-made antibodies, so protection is immediate, but no memory cells are formed and the transferred antibodies are degraded within weeks to months, after which protection ends completely.
Crossing that with the second criterion gives four cases. Natural active immunity follows recovery from an infection. Artificial active immunity follows vaccination, which supplies antigen without disease. Natural passive immunity is the transfer of maternal antibodies across the placenta and in breast milk, protecting an infant whose own adaptive system is immature. Artificial passive immunity is the injection of prepared antibodies — antivenom, or immunoglobulin given after a rabies or tetanus exposure.
The two criteria together predict which is appropriate in a given situation. Someone bitten by a venomous snake needs protection now and cannot wait weeks, so passive immunity is the only option — and because it confers no memory, a second bite requires antivenom again. Someone at future risk should receive a vaccine, since active immunity takes time to develop but then persists. This is why post-exposure treatment for tetanus can involve both at once: immunoglobulin for immediate protection, and vaccine for lasting immunity.
Two independent questions generate the four categories: whose immune system produced the antibodies — active immunity meaning the individual's own system responded and produced them, passive meaning antibodies made elsewhere were transferred in — and how the exposure occurred, naturally through ordinary living or artificially through deliberate intervention. The first criterion has large consequences: active immunity involves clonal selection so memory cells are produced and protection is long-lasting, often lifelong, but it takes days to weeks to develop and cannot help someone already exposed, whereas passive immunity supplies ready-made antibodies so protection is immediate, but no memory cells form and the transferred antibodies degrade within weeks to months, after which protection ends completely. Crossing that with the second criterion gives four cases: natural active immunity follows recovery from infection; artificial active immunity follows vaccination, which supplies antigen without disease; natural passive immunity is the transfer of maternal antibodies across the placenta and in breast milk, protecting an infant whose own adaptive system is immature; and artificial passive immunity is the injection of prepared antibodies, such as antivenom or immunoglobulin given after a rabies or tetanus exposure. The two criteria together predict which is appropriate: someone bitten by a venomous snake needs protection immediately and cannot wait weeks, so passive immunity is the only option, and because it confers no memory a second bite requires antivenom again, while someone at future risk should receive a vaccine, since active immunity takes time to develop but then persists — which is why post-exposure treatment for tetanus can involve both at once, immunoglobulin for immediate protection and vaccine for lasting immunity.
Evaluate vaccination programs as a strategy for controlling infectious disease in a population.
Evaluate demands a judgement against criteria and a position that commits. The question is about programs in a population, so the judgement is epidemiological rather than about whether vaccines work in an individual.
Plan: state the criteria, put the case for, put the case against, reach a verdict, then qualify it.
Vaccination programs will be judged on the reduction in disease they achieve, on whether that reduction extends to people who are not vaccinated, and on their cost and risk relative to the alternatives.
The evidence is exceptionally strong. Smallpox was eradicated globally by vaccination, and polio has been eliminated from all but a few countries; measles, diphtheria and whooping cough incidence fell by orders of magnitude following program introduction, in each case before any comparable change in living conditions. Programs also protect beyond those vaccinated: when a large enough proportion is immune, an infected person is unlikely to meet a susceptible one, so transmission chains break and infection cannot establish — which is herd immunity, and it protects newborns, the immunosuppressed and those for whom vaccination is contraindicated.
Programs are also among the most cost-effective interventions in public health, since preventing a case costs far less than treating one, and the cost of a program falls as the disease becomes rare. This creates the paradox that programs become better value at exactly the point where the disease is least visible.
Several limitations are real. Coverage must be high and sustained, and the threshold depends on how contagious the disease is — measles requires roughly ninety-five per cent, which is difficult to maintain. No vaccine is perfectly effective or perfectly safe, so a rare adverse event occurs in someone who would not otherwise have been ill, and public tolerance for that risk falls as the disease becomes invisible. Some pathogens defeat the approach: influenza changes antigenically each season, and HIV mutates too fast for any vaccine yet achieved. Cold chain and delivery costs also make coverage hardest where disease burden is highest.
Vaccination programs are the most effective population-level control strategy available for the diseases they can address, and their limits are set by pathogen biology and by coverage rather than by the principle. They should be judged as a collective intervention rather than an individual one, since their distinctive achievement — herd immunity — cannot be produced by individuals acting separately, and that is precisely what falling coverage removes first.
The qualification is that a program's success undermines its own support. When a disease becomes rare, the visible risk shifts from the disease to the vaccine, so the rational-seeming individual calculation changes even though the population calculation does not — which is why measles has returned in communities where coverage fell, and why sustaining a program requires maintaining confidence as much as maintaining supply.
Vaccination programs will be judged on the reduction in disease they achieve, on whether that reduction extends to the unvaccinated, and on cost and risk relative to alternatives. The evidence is exceptionally strong: smallpox was eradicated globally by vaccination and polio eliminated from all but a few countries, while measles, diphtheria and whooping cough incidence fell by orders of magnitude following program introduction, in each case before any comparable change in living conditions — and programs protect beyond those vaccinated, since when a large enough proportion is immune an infected person is unlikely to meet a susceptible one, so transmission chains break, which is herd immunity and protects newborns, the immunosuppressed and those for whom vaccination is contraindicated. They are also among the most cost-effective public health interventions, since preventing a case costs far less than treating one and program cost falls as the disease becomes rare — creating the paradox that they become better value exactly where the disease is least visible. Several limitations are real: coverage must be high and sustained, with the threshold depending on contagiousness, around ninety-five per cent for measles, which is difficult to maintain; no vaccine is perfectly effective or safe, so rare adverse events occur in people who would not otherwise have been ill, and tolerance for that risk falls as the disease becomes invisible; some pathogens defeat the approach, since influenza changes antigenically each season and HIV mutates faster than any vaccine yet achieved; and cold chain and delivery costs make coverage hardest where burden is highest. Vaccination programs are therefore the most effective population-level control strategy available for the diseases they can address, their limits set by pathogen biology and coverage rather than by the principle, and they should be judged as a collective intervention rather than an individual one, since herd immunity cannot be produced by individuals acting separately and is what falling coverage removes first. The qualification is that success undermines support: as a disease becomes rare the visible risk shifts from the disease to the vaccine, so the individual calculation appears to change even though the population one does not — which is why measles has returned where coverage fell, and why sustaining a program means maintaining confidence as much as supply.
Practise independently
Attempt at least one response in your own words. Model answers support checking; they do not replace the attempt.
A fresh set drawn from this lesson's question bank, feedback shown immediately. +5 XP per correct · +25 XP all correct
Pick your answer, then rate your confidence, that tells the system what to drill next.
UnderstandBand 3(3 marks) 1. Using two specific examples, explain the difference between natural passive immunity and artificial passive immunity. For each, describe how the antibodies are acquired and explain why protection is temporary.
1 mark: natural passive, example and mechanism · 1 mark: artificial passive, example and mechanism · 1 mark: why both are temporary (no memory cells; antibodies catabolised)
UnderstandBand 4(3 marks) 2. Explain the concept of herd immunity, including how the herd immunity threshold is determined and why it differs between diseases. Use measles and polio as examples.
1 mark: herd immunity defined · 1 mark: threshold determined by R₀ (1 − 1/R₀) · 1 mark: measles vs polio comparison
EvaluateBand 5(4 marks) 3. Evaluate the effectiveness of global polio vaccination programs, referring to the historical reduction in cases, the current status of eradication efforts, and the barriers that have prevented complete eradication.
1 mark: quantitative evidence (350,000/year in 1988 → fewer than 100 a year now) · 1 mark: current status (endemic only Pakistan/Afghanistan) · 1 mark: barriers (conflict, distrust, logistics, not vaccine failure) · 1 mark: overall evaluative conclusion
Show all answers
Multiple choice
MC answers and full explanations are shown inline as you complete each question. Use the retry button to attempt a fresh set from the lesson bank.
Short Answer Model Answers
Q1 (3 marks): Natural passive immunity occurs when pre-formed antibodies are transferred from one individual to another through a natural biological process, without medical intervention and without the recipient's immune system being activated. An example is the transfer of IgG antibodies from a pregnant mother to her foetus across the placenta during the third trimester, protecting the newborn before its own immune system matures. Artificial passive immunity occurs when pre-formed antibodies are deliberately administered through a medical procedure. An example is antivenom, antibodies produced in horses or sheep exposed to snake venom; when injected into a snakebite victim, they immediately neutralise circulating toxins. Both are temporary because in neither case does the recipient's immune system mount its own response, no clonal selection, no plasma cells, no memory B or T cells. The transferred antibodies are gradually catabolised over weeks to months, and protection fades as their concentration declines.
Q2 (3 marks): Herd immunity occurs when a sufficient proportion of a population is immune (through vaccination or prior infection) that the pathogen cannot find enough susceptible hosts to sustain transmission chains, protecting even non-immune individuals indirectly. The threshold is determined by the basic reproduction number (R₀): threshold = 1 − 1/R₀. A higher R₀ means each infected person infects more people, so a larger proportion must be immune. Measles has an R₀ of 12–18, giving a threshold of ~93–95%, one of the highest of any human pathogen. Polio has an R₀ of 5–7, giving a threshold of ~80–85%. This is why measles outbreaks occur rapidly when coverage drops even a few percent, while polio can be controlled at lower coverage levels.
Q3 (4 marks): The global polio vaccination program (WHO Global Polio Eradication Initiative, launched 1988) has been one of the most successful public health interventions in history. In 1988 polio was endemic in 125 countries and paralysed ~350,000 children per year; by 2023 wild poliovirus type 1 was endemic in only Pakistan and Afghanistan, with just 12 cases globally (99 in 2024), a reduction of more than 99.9%. Multiple regions have been certified polio-free (Americas 1994, Western Pacific including Australia 2000, India 2014). The barriers preventing complete eradication are non-biological: armed conflict disrupts campaigns and displaces populations; misinformation (e.g. false sterilisation claims) generates distrust; vaccination workers have been attacked. The vaccine itself is effective, there is no animal reservoir, and the virus does not mutate fast enough to escape immunity. Overall, the program represents an extraordinary success, the final 0.1% is a governance and security challenge, not an immunological one.
Retrieve and reflect
Use the Review session first, then compare how your thinking changed.
A full module quiz covering every lesson in this module, not just this one. Set aside a decent block of time and treat it like a real assessment.
Start the module quiz →You were asked what a successful mass vaccination program actually does to a disease at the population level. Jonas Salk's 12 April 1955 announcement gives the empirical answer: 1.8 million 'Polio Pioneers' vaccinated across 44 US states produced US polio cases dropping from 58,000 in 1952 to 5,600 in 1957 to just 61 in 1965, not because all susceptible people were vaccinated, but because enough of the population was immunised to interrupt transmission chains.
The answer: vaccination changes the proportion of susceptible individuals in the population. Below the herd immunity threshold, the pathogen can find enough susceptible hosts to sustain transmission, each infected person, on average, infects at least one other. Above the threshold, transmission chains break, infected individuals are increasingly surrounded by immune people who cannot be infected, and the chain dies out. The pathogen's "reproductive rate" effectively falls below 1.
As vaccination coverage rises through the threshold, the effect on case numbers is non-linear, a small increase in coverage near the threshold produces a disproportionately large reduction in cases. This is why the measles data in Activity 2 shows dramatic drops near the 95% threshold. And it explains why small drops in coverage below the threshold produce rapid outbreaks, the pathogen's effective reproduction number crosses back above 1.
If you predicted "fewer people get sick", correct at the individual level. The population-level insight is that the pathogen's ability to persist depends entirely on finding susceptible hosts. Enough immunity in a population and the virus simply runs out of places to go.